Understand your injury.
Choose a condition to read what is damaged, how it is diagnosed, what to try before surgery, and how long recovery takes. These are the conditions we see most often, not a complete list of everything we treat. If yours is not here, call the office.
Patellar tendon rupture
A pop while landing or lifting, and you cannot straighten the knee or stand on it.
The patellar tendon connects the kneecap to the shin bone and is the final link in the mechanism that straightens your leg. When it ruptures — usually from a forceful eccentric load with the knee bent, such as landing from a jump or catching a fall — the extensor mechanism is broken. The kneecap rides upward, a gap can often be felt below it, and the knee gives way immediately. Risk is higher with prior tendon degeneration, previous patellar tendon graft harvest, chronic steroid use, and some systemic conditions.
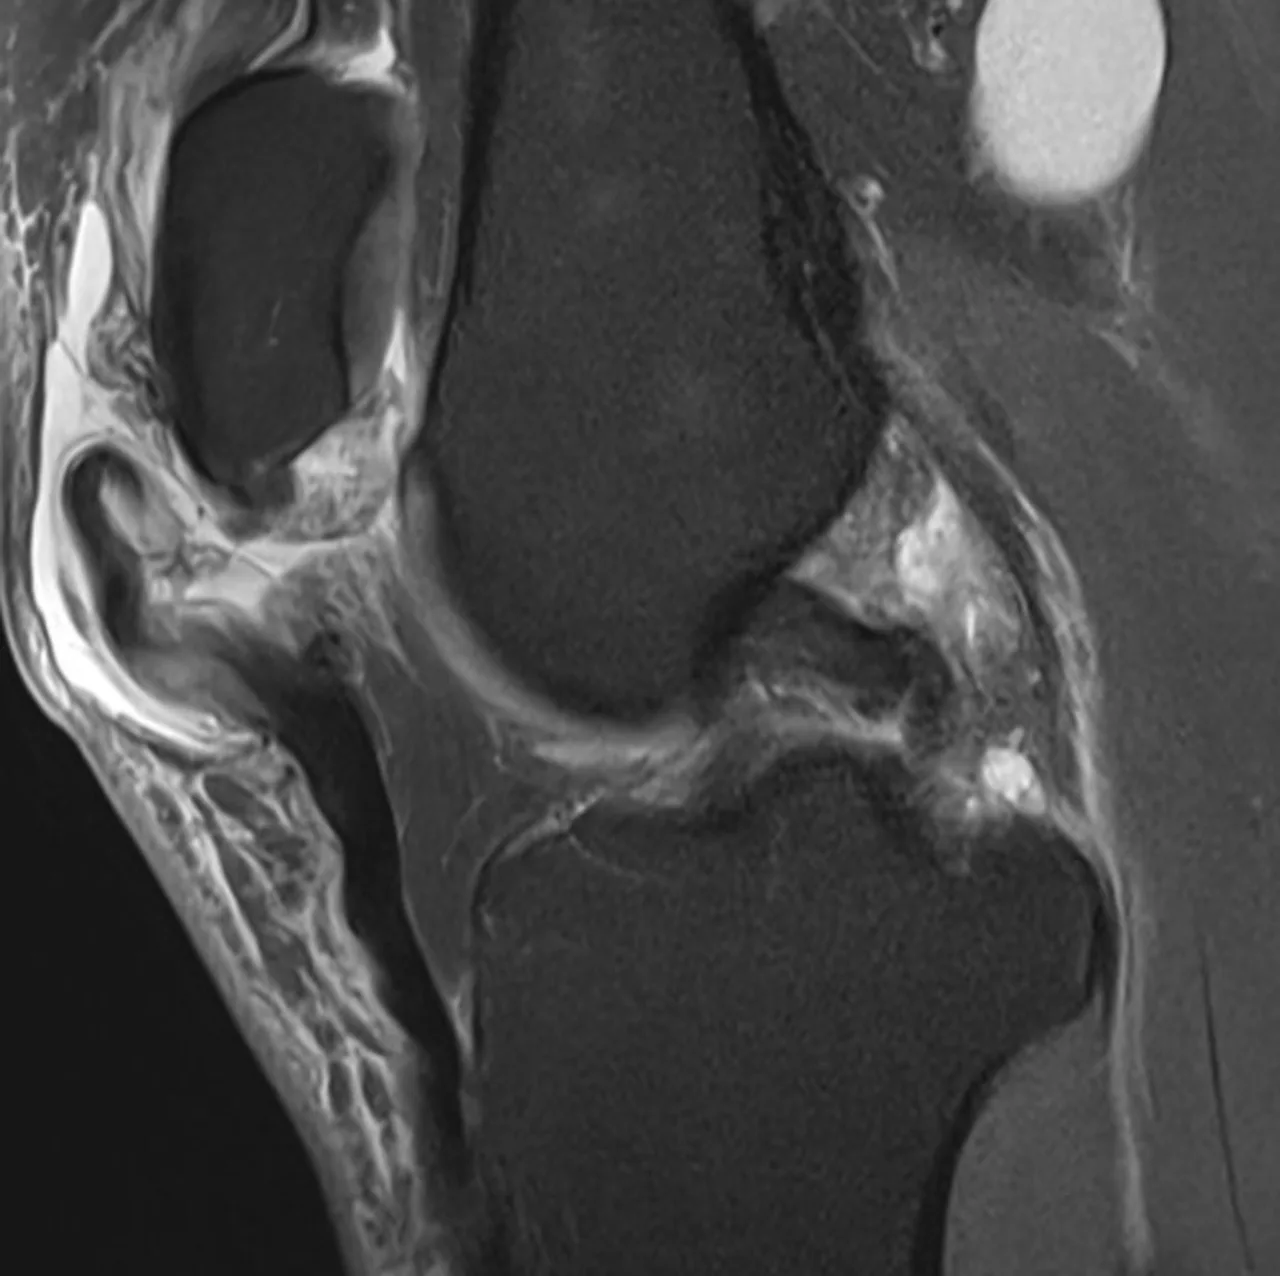
The defining test is whether you can actively straighten the knee or hold it straight against gravity — with a complete rupture, you cannot. A palpable gap below the kneecap is common. X-rays show the kneecap sitting high (patella alta). Ultrasound or MRI confirms whether the tear is partial or complete and how far the tendon has retracted.
Only appropriate for a partial tear with an intact extensor mechanism — someone who can still perform a straight leg raise. That is treated in a brace locked in extension with progressive motion and quadriceps rehabilitation.
A complete rupture is a surgical injury, and it is time-sensitive. When it is repaired within the first two to three weeks, the tendon ends come together cleanly; if it is left longer, the tendon retracts and scars, and reconstruction with a graft may be required. This is one of the few orthopaedic problems where waiting materially worsens the operation.
The tendon is repaired back to the bottom of the kneecap. Dr. Jiang uses suture anchors, small implants placed in the bone that hold strong sutures, rather than drilling tunnels through the kneecap. This gives a stronger repair, so protected motion can begin early. The repair is often reinforced with an extra suture. Outcome depends closely on how early the repair is done and on following the quadriceps rehabilitation program.
- Is my tear complete, and how soon does it need to be repaired?
- How much has the tendon retracted?
- What quad strength do I need before I'm cleared?
These pages describe how these injuries are generally evaluated and treated. They are not a diagnosis and not medical advice. Two people with the same MRI finding can need completely different plans — that is what the visit is for.